


Can Lean Improve Spinal Fusion Surgery? Is This the Right Definition or Use of PDSA?
Here's a blog post written by three physicians:
 The AHRQ website I linked to above almost seems to imply that “Plan” involves proposing a solution without enough understanding of the current state:
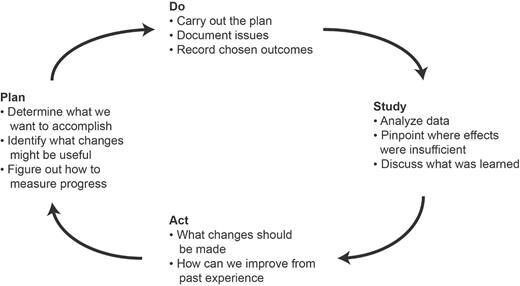 I'd suggest that “Determine what we want to accomplish” should really start with a problem statement. I see many cases where “PDSA” improvement work at a hospital starts with an “aim statement” that jumps to a solution.
I think “We aim to reduce post-operative infections by 50%” is a better aim statement than “We aim to implement ________________.
Their “Do” phase does say “carry out the plan” — so I think the blog post somehow ended up being a poor distillation of the journal article?
But the journal article's “problem statement” includes a solution:
 Unless I'm missing something or misreading the article, the stated results of the PDSA are basically limited to current state analysis.
What seems to be missing is:
Can the auto industry improve spinal fusion surgery?
It's interesting that they so closely associate Lean with the auto industry when, at this point, Lean is used in virtually every industry and setting. That's why I used the word “Lean” in the title of my blog post here. They are also authors of a journal article titled “Application of Lean Principles to Neurosurgical Procedures: The Case of Lumbar Spinal Fusion Surgery, a Literature Review and Pilot Series,” published in Operative Neurosurgery. The conclusion from their journal article:I'd suggest that Lean doesn't just “identify waste.” I'd expect (or hope) that an article like this would talk not just about identifying waste but also reducing waste. PDSA is, of course, the Plan-Do-Study-Adjust mindset and process. You often see different definitions of the PDSA cycle (or PDCA, Plan-Do-Check-Act). I was taught (and teach) that the steps are:CONCLUSIONThis pilot series demonstrates that lean principles can standardize surgical workflows and identify waste. Though time and labor intensive, lean principles and PDSA methodology can be applied to operative steps, not just the perioperative period.
- Plan: Understand the current situation and develop a hypothesis about a change to try
- Do: Do a small pilot, a test of change, to see what happens
- Study: Study the effects of the change. Did you get the expected results? Were there side effects?
- Adjust: Adjust the plan, if necessary, and continue the PDSA cycles (or adopt the change and move forward to another improvement)
The AHRQ website I linked to above almost seems to imply that “Plan” involves proposing a solution without enough understanding of the current state:
Plan: Here you will write a concise statement of what you plan to do in this testing. This will be much more focused and smaller than the implementation of the tool. It will be a small portion of the implementation of the tool.I think we have to be careful about jumping to solutions. Lean really emphasizes understanding the problem, need, or opportunity first. AHRQ's remaining PDSA steps are:
- Do: “execute [the plan] or set it in motion”
- Study: “…study the results. What did you learn? Did you meet your measurement goal?”
- Act: “What did you conclude from this cycle?”
A main process improvement tool used by medical practitioners to improve the value of healthcare is Lean production and was adapted from the Toyota Motor Corporation. Lean production philosophy is simple; it empowers all individuals contributing to a process to identify potential intrinsic waste and eliminate it while optimizing the product.It's good that they emphasize empowering individuals. Toyota would talk about that. I wouldn't use the word “optimize” though. As an industrial engineer, I was taught that the word “optimize” has a particular mathematical meaning. Optimization implies the absolute best choice or outcome, whereas Lean is more of a process of continually finding “better” even though we might not ever reach “best.” I do wish the authors hadn't used a limited definition of Lean as “process improvement.” Toyota describes the Toyota Production System (a.k.a. “Lean”) as technical methods, a managerial approach, a philosophy, and a culture — it's an integrated system.
Toyota Production System Explained: Why Philosophy Matters More Than ToolsThe authors focus on efficiency:
Lean principles have been very effective in decreasing inefficiencies in mass production.Lean has ALSO been very effective in reducing defects (or improving quality). Toyota defines TPS as dual pillars of “flow” and “built-in quality.” Those concepts are intertwined. Lean isn't just about speed, efficiency, flow, or cost. I think the authors also misstate the PDSA cycle, as they write:
We began in the Plan phase by creating a process map where we defined similar modular steps within each surgical procedure. This included the surgical exposure, discectomy/decompression (removing the intervertebral disc or removing parts of the bone which are causing symptomatic compression of nerves), hardware placement, and surgical closure. The Do phase involved tracking the time and waste for each modular step. In the Study phase, we analyzed these results, and in the Act phase we implemented improvement strategies.To summarize their view:
- Plan: Study the current state (that's a good thing to do, don't get me wrong
- Do: This data collection sounds like a continuation of the Plan step, as they weren't yet testing their countermeasures
- Study: They say they “analyzed the data” — this step should actually be “analyzing the results of the test of change”
- Act: They implemented the strategies
I'd suggest that “Determine what we want to accomplish” should really start with a problem statement. I see many cases where “PDSA” improvement work at a hospital starts with an “aim statement” that jumps to a solution.
I think “We aim to reduce post-operative infections by 50%” is a better aim statement than “We aim to implement ________________.
Their “Do” phase does say “carry out the plan” — so I think the blog post somehow ended up being a poor distillation of the journal article?
But the journal article's “problem statement” includes a solution:
“Lumbar spinal fusion surgery is heterogeneous, using varied approaches and multiple vendors. The non-standardization of surgery causes inventory, motion, waiting and over-processing wastes. By standardizing the procedural steps of the operation, we will reduce operative time and reduce cost.“Again, I'd prefer to state the problem in terms of outcomes. The last sentence of the “problem statement” seems like a hypothesis (and a fine one). The second sentence is some causal analysis. I prefer to see:
- Problem statement
- Causal analysis
- Proposed countermeasure
Unless I'm missing something or misreading the article, the stated results of the PDSA are basically limited to current state analysis.
What seems to be missing is:
- What changes did they make?
- What were the results of those changes?
FREE GUIDE FOR LEADERS
Just PDSA It
Kaizen, A3 problem solving, and strategy deployment are the same learning loop at three sizes. This free guide shows how to size the method to the problem, why “just do it” skips the part that teaches you something, and what leaders can do to make being wrong cheap enough that people run honest tests.
18 pages, with one thing to try at your next approval meeting. The download link appears as soon as you enter your email.







The doctor’s blog post and your analysis of it shows that it is difficult for people to understand the thinking and methods that make for effective process improvement work. Imprecision in thinking and leads to faulty application which leads to lesser results. In recent years, I have been hearing more people say that “Lean is complicated” (vs. what people more commonly used to say: “Lean is common sense”). Perhaps this is just an excuse for poor results. But, empirical observation of outcomes over many years indicates that this may be more true than not. As an professional educator, it is a constant challenge to teach the correct way of thinking — let alone the correct application of the method. That’s why I rely heavily on visual controls for students to use one-the-job after the course is over.
I was thrilled in reading this to find out these MDs were writing about how in their view, lean does work, rather than doesn’t work, in the OR. I was expecting the latter for some reason, so maybe I’m having a pessimistic Monday. It’s great that they’ve gotten excited about lean’s potential, even if they’re in off base in some of the explanation. They actually do including “eliminating waste” in their lean definition, in another paragraph — “to identify potential intrinsic waste and eliminate it while optimizing the product”. Their explanation suggests they did implement some changes to their process, but they don’t describe them or the results. Their PDSA diagram is much better than their explanation. The “Plan” in that diagram includes identifying measures, but they don’t offer any in this article, so they haven’t told us how they’ll know if they improved. I hope they keep going and enlist the help of a lean coach to help with results and learning.
Tom – Yes, I was thrilled by the headline. But, then I realized they were talking about potential improvement as opposed to actual improvement. I’m surprised they published about current state analysis instead of waiting to describe results.
I guess I wonder if there is enough pragmatism in PDCA. Plan.Do, then check !Human bodies are not Cars that can be replaced.
Human bodies are important, so one could argue that PDSA is better and more humane than just Plan Do. We need continuous improvement in healthcare. Otherwise, the status quo means that people keep dying due to preventable medical error.
Doctors know PDSA works. They’ve been using PDSA since before it was called PDSA. They’ve been using it since before Toyota operated their first loom. The level of deliberate rigour within healthcare (due to both risk and regulation) is largely the only difference.
We lose so many opportunities to learn and improve when we emphasize the wrong word in the question, “why are they doing it like that?”. Its the opposite of being open to learning. It is the opposite of continuous improvement.
Lean isn’t going to die because it doesn’t work. Lean is going to die due to the pervasive arrogance and spectacular lack of humility from it’s practitioners.