Examples of Waste in Healthcare: The Eight Lean Categories
These examples of waste in healthcare show how missing supplies, unnecessary movement, delays, and rework interfere with patient care. I use the eight Lean waste categories to help teams describe those problems and decide what to improve.
Jump to an example: Defects | Overproduction | Transportation | Waiting | Inventory | Motion | Overprocessing | Wasted Human Potential.
>What are the problems and annoyances that constantly appear, interfering with our work and the best patient care? In Lean, we call this waste. Dr. Don Berwick describes waste as a “needless hassle” and “what does not make sense in our health care system.”
Why These Examples of Waste in Healthcare Matter
Historical studies discussed in Lean Hospitals found that medical-surgical nurses spent about 30% of their time on direct patient care. That figure is not a current benchmark for every hospital, and time away from the bedside is not automatically waste. Direct care includes:
- Nursing procedures
- Hygiene and toileting
- Administering medication
- Giving medical guidance
And the studies that generated those results were done before the widespread adoption of electronic medical record (EMR) systems. EMR systems may solve some problems, but new technologies sometimes create new forms of waste and keep providers away from the bedside even more than before.
Reducing avoidable work can free time for patient care and reduce frustration. That does not establish that a unit has enough staff. Teams need to examine workload, staffing, and process problems together, rather than treating Lean as a reason to ask fewer people to do more.
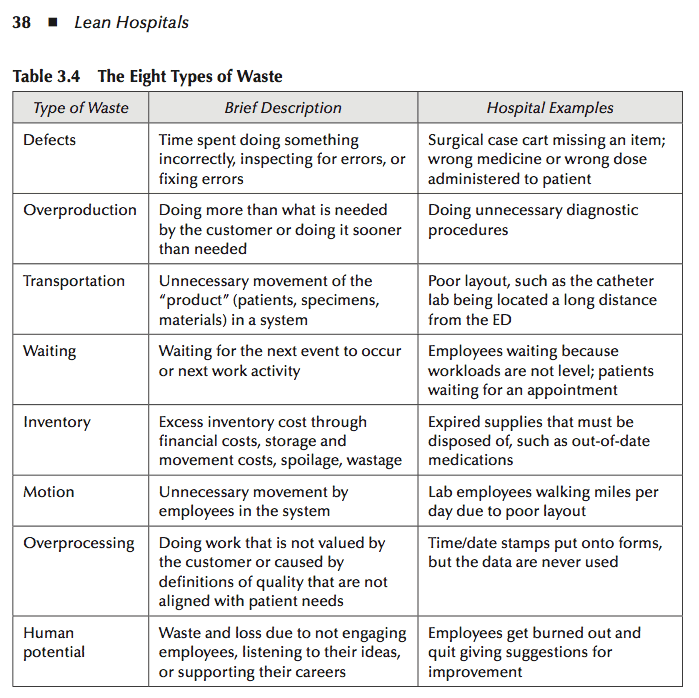
To help identify waste, having specific shared terminology can help. Ohno defined seven types of waste, while later publications often listed eight types. These definitions have been adopted as a useful framework for viewing waste in hospitals. Sometimes, the terms are used verbatim; sometimes, they are modified. Having complete agreement on the exact terms is not crucial, as Toyota did not intend this list to be all inclusive or to be something that could not be changed. Consistent terminology does, however, help us communicate within our organization and across the industry.
Hospital workdays are full of interruptions, miscommunications, wasted motion, and workarounds. When supplies are missing, we run to find them. When workspaces are badly designed, we walk faster and try harder. When orders don’t arrive from a physician’s office, we make multiple phone calls to track them down. It’s good, in a way, that people make this effort. But they shouldn’t have to. These workarounds don’t prevent the same problem from happening again tomorrow.
The DOWNTIME mnemonic. Many Lean practitioners remember the eight wastes through the acronym DOWNTIME: Defects, Overproduction, Waiting, Non-utilized talent, Transportation, Inventory, Motion, and Extra-processing. The order below follows Ohno’s original sequence rather than the mnemonic.
Learning to separate motion (the things we do) from value (the things we do that help the patient) is a critical step. Lean gives us a framework for seeing that difference clearly — and a shared language for talking about it.
Taiichi Ohno at Toyota originally defined seven types of waste. Later publications added an eighth: wasted human potential. These categories aren’t meant to be rigid or exhaustive — Toyota never intended them that way. They’re a starting point for seeing work differently.
The examples below are drawn from my book Lean Hospitals and from real organizations that have applied these ideas.
Defects
A surgical case cart arrives in the operating room missing an instrument. A patient receives the wrong dose of a medication. A form gets filled out incorrectly and has to be redone. In healthcare, defects mean any work not done right the first time — including the time spent inspecting for errors and fixing them. Some defects are minor inconveniences. Others injure or kill patients.
At one hospital, the anatomic pathology lab couldn’t always find tissue slides that needed re-reading. When a slide went missing, technicians had to locate the original tissue block, recut it, and start over — more time, more labor, more cost, and more delay for the patient.
Overproduction
Unnecessary testing is one form of overproduction. The historical examples discussed in Lean Hospitals include the following: At the University of Utah Health Care, the hospital started requiring residents to justify each test and saved $200,000 a year. At one hospital pharmacy, 480 medications were returned to the pharmacy every day — more than one per admitted patient — because orders had changed or patients were discharged before the medications were administered. Pharmacy staff spent 11 hours a day processing those returns.
Overproduction means doing more than the patient needs or doing it sooner than necessary. In healthcare, that includes unnecessary diagnostic procedures, “just-in-case” blood draws that go unused more than 90% of the time, and the overproduction of reports nobody reads. One hospital’s chief clinical officer discovered more than 320 different reports being generated daily or annually, with no formal process for deciding whether any of them were still useful.
Transportation
One hospital used Lean methods to follow a 74-year-old woman from arrival to surgery. During the course of her visit, she walked the equivalent of five and a half football fields. Transportation waste is any unnecessary movement of patients, specimens, or materials through the system.
Park Nicollet Health Services in Minnesota designed its Frauenshuh Cancer Center so that patients stay in a single room for nurse and doctor visits, lab draws, treatment, and other support services. The care comes to the patient instead of the patient walking between departments.
Waiting
Patients wait for appointments, for test results, for a bed to open up, for discharge paperwork. But employees wait too — for information, for equipment, for the next patient to arrive. At one neurology department, all but the most urgent patients waited a long time for an appointment, even though the neurologists often concluded the referral had been unnecessary. Each inappropriate referral meant a patient who actually needed the consult had to wait longer.
Waiting is time when nothing value-added is happening. It is probably the most visible type of waste in any hospital.
Inventory
Expired supplies sitting on shelves. Out-of-date medications that have to be disposed of. Surgical kits that contain instruments the surgeon never uses — sterilized repeatedly and never opened.
In one hospital, a central supply cabinet system led nurses to hoard supplies in drawers, lockers, and pockets because the cabinet was inconvenient to access. The hospital started reconsidering which items truly needed tight control and which could be stocked closer to the point of care. The trade-off matters: if items are inexpensive and don’t take up much space, storing them in more locations often reduces total waste in the system.
Motion
Motion waste includes searching for supplies, hunting for equipment, and walking between workstations because of poor layout. Observing that work with staff helps distinguish necessary movement from movement that could be prevented.
In one hospital, lift assists for patients were stored in a closet on a different floor because the unit didn’t have enough storage space. Because it was inconvenient and time-consuming to go get the proper equipment, nurses often lifted patients without the assist — increasing the risk of employee injuries and patient falls. The unit used 5S to free up space and relocated the lifts, reducing walking and ensuring the right equipment was actually used.
The following are historical improvement examples discussed in Lean Hospitals, rather than current performance claims. Seattle’s Virginia Mason Medical Center used Lean methods to increase nursing time at the bedside from about 33% to 90%. The National Health Service in the United Kingdom has taught Lean methods to nurses and hospital staff through its Releasing Time to Care program. On average, time at the bedside increased from 35% to 55% across 19 NHS Scotland hospitals that implemented the program. Hospitals in the United States are using a similar approach called Transforming Care at the Bedside (TCAB), which sets a goal of increasing bedside time from 30% to 70%. One system that adopted TCAB reported the time nurses spent in patient rooms increased from 2.5 hours in a 12-hour shift to 6.5 hours, resulting in a 32% reduction in falls and a 17% reduction in medication errors. Nurse turnover rates in TCAB hospitals fell by nearly 20%, suggesting that an environment with less waste and more time for patient care is more rewarding for staff.
Overprocessing
In one hospital’s surgery department, an employee spent three hours a day folding towels after they came back from the laundry. Nurses upstairs were immediately unfolding them and laying them flat. Nobody had asked.
Overprocessing is doing work that provides no value to the patient — entering data into systems nobody reads, clicking through excessive EMR warnings, running centrifuges longer than the manufacturer recommends out of habit. It often results from miscommunications in the handoffs between people or departments. In a billing department, one employee removed “extra” copies from patient charts to save storage space while the next employee in the process walked to the copier to recreate them.
Wasted Human Potential
At one hospital, a nurse said the initial Lean work was “the first time in six years that anybody has asked me what I think about anything.”
This eighth type of waste — sometimes called the waste of talent — is what happens when organizations fail to engage people’s minds. It includes skilled professionals doing work below their training level: nurses doing tasks that could be handled by nursing assistants, pharmacists doing work that pharmacy techs could do. It also includes the subtler loss that occurs when employees stop offering ideas because they’ve learned nobody is listening. One laboratory technologist with more than 25 years of experience said, “Nowadays, I feel like a robot.” Managers had rarely asked for opinions or ideas. Through Lean, employees can have their intelligence and creativity put to use, even when the hands-on work itself has become highly automated.
Use the Examples to Investigate One Recurring Problem
Ask a team to choose one recurring delay or workaround. Observe what happens, ask what makes the work difficult, and test a small change with the people affected. Check whether it helps patients and staff without creating a problem elsewhere. The categories are a way to start that conversation; agreeing on a label is less important than understanding the work.
For a broader introduction, see my guide to the eight wastes of Lean. For the next step, these daily healthcare kaizen examples show how teams document and share improvements.
Frequently Asked Questions
What are the eight types of waste in healthcare?
The eight types of waste are defects, overproduction, transportation, waiting, inventory, motion, overprocessing, and non-utilized talent. The first seven come from Taiichi Ohno’s original framework at Toyota. The eighth — wasting people’s talent and ideas — was added later and matters enormously in healthcare, where the people are the product.
What is the most common type of waste in hospitals?
The mix varies by department and process. Waiting and unnecessary movement are often visible, but teams should observe their own work rather than assume one category is always the largest.
What is an example of overproduction waste in healthcare?
Ordering diagnostic tests that aren’t medically necessary is a common example. So is preparing medications that go unused when a patient’s orders change or they’re discharged before the medication is administered.
What is the waste of non-utilized talent in healthcare?
It’s what happens when skilled people spend their time on work below their training level — nurses doing tasks that could be handled by nursing assistants, pharmacists doing work that pharmacy techs could do. It also includes the waste of not asking employees for their ideas. At one hospital, a nurse said the initial Lean work was “the first time in six years that anybody has asked me what I think about anything.”
How can hospitals reduce waste without cutting corners on patient care?
Work with clinicians and staff to remove delays, rework, and other avoidable steps while checking safety, quality, and workload. Reducing waste does not by itself establish that staffing is adequate.
What does DOWNTIME stand for in Lean?
DOWNTIME stands for Defects, Overproduction, Waiting, Non-utilized talent, Transportation, Inventory, Motion, and Extra-processing. It is one way to remember the categories.
How do you identify waste in a hospital?
Go to where the work happens, observe with the people doing it, and ask about recurring delays and workarounds. Process mapping and time studies can also help. The categories give teams a vocabulary for what they find.
Read a sample before deciding
Lean Hospitals explores how to improve quality, patient safety, and daily work. Read the first chapter to see whether the approach fits the problems your team is working on.